
Heel Prick Screening
11 Sept 2026 · 36 min read
On this page28 sections
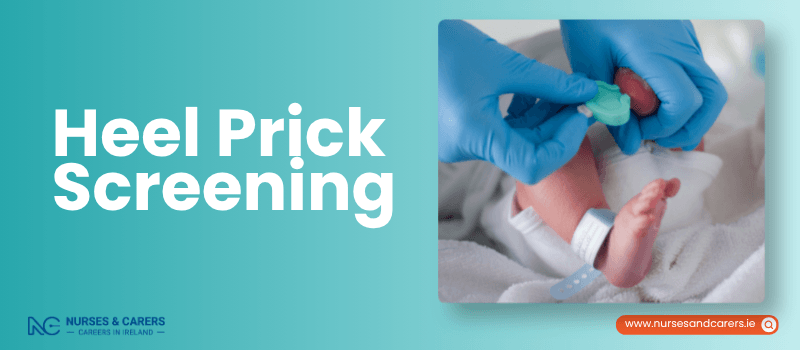
The newborn bloodspot screening, commonly referred to as the heel prick screen, is a safe, vital health check offered to all babies born in Ireland. The test is completely free, and 99.9% of parents choose to participate to ensure their child's health from the earliest stages of life.
Procedure and Timing
When: The screen is ideally performed when the infant is between 3 and 5 days old. This precise window ensures the baby has been feeding long enough to provide accurate metabolic markers, while still catching conditions before they cause rapid illness.
Who & Where: A qualified midwife or Public Health Nurse (PHN) performs the procedure either in the hospital before discharge or during a scheduled visit at your home.
How: The practitioner collects a small, safe sample of blood by gently pricking the baby's heel. The procedure is designed to collect the necessary blood spots efficiently with minimal, brief discomfort to the infant.
The 11 Conditions Screened
Laboratory specialists analyze the blood spot sample to detect 11 rare but serious conditions. Most babies will test negative for all of them. These conditions include:
Cystic Fibrosis (CF): A genetic condition affecting the lungs and digestive system.
Congenital Hypothyroidism (CHT): A deficiency in thyroid hormone affecting growth and development.
Phenylketonuria (PKU): A metabolic disorder involving the inability to break down an amino acid called phenylalanine.
Classical Galactosaemia (C Gal): An inherited inability to correctly process the sugar galactose.
Glutaric Aciduria Type 1 (GA1): A metabolic disorder causing a toxic buildup of specific organic acids.
Medium-Chain Acyl-CoA Dehydrogenase Deficiency (MCADD): A condition where the body cannot properly convert certain fats into energy.
Homocystinuria (HCU): A metabolic disorder affecting the processing of the amino acid methionine.
Maple Syrup Urine Disease (MSUD): An inherited inability to process certain protein building blocks (amino acids).
ADA-SCID & SCID: Severe Combined Immunodeficiencies that compromise the immune system’s ability to fight off infections.
Spinal Muscular Atrophy (SMA): A genetic neuromuscular disorder causing progressive muscle wasting and weakness.
Key Benefits of Early Screening
The vast majority of these 11 conditions present no obvious signs or physical symptoms immediately after birth, and most affected infants have no known family history of the disorder.
Early Detection: Identifying these risks before physical symptoms emerge allows medical teams to intervene immediately.
Timely Treatment: Starting clinical treatment as soon as possible drastically improves long-term health outcomes, prevents severe physical or intellectual disabilities, and saves lives.
Understanding the Limitations: The "Sieve" Analogy
No screening test is entirely flawless. The heel prick test is not a final medical diagnosis; it simply filters out which babies require deeper medical investigation.
Think of the screening process like passing a population through a clinical sieve:
The Majority (Passed Through): Most babies pass cleanly through the sieve. This indicates a "normal" or low-risk result, meaning they are highly unlikely to have the conditions.
The Minority (Caught in the Sieve): A small number of babies remain in the sieve. This is a "suspected" or positive screening result indicating a higher risk. If your baby's sample indicates a risk, a doctor or nurse will contact you immediately to arrange specialized diagnostic tests.
False Positives: Further testing will reveal that some babies who were "caught in the sieve" do not actually have the condition.
False Negatives: In exceptionally rare cases, a condition can "slip through the sieve" undetected, meaning a baby receives a normal screening result despite having the condition.
Heel prick screening checks for 11 rare but serious conditions in babies. It is also known as 'newborn bloodspot screening'.
1. ADA-SCID: heel prick screening
Adenosine Deaminase Deficiency Severe Combined Immunodeficiency (ADA-SCID) is an exceptionally rare, inherited genetic condition passed from parents to children. It is a highly serious disorder that causes a profound failure of the child's immune system.
The Underlying Cause and Impact
The condition occurs when a vital enzyme called adenosine deaminase is either entirely missing or fails to function correctly.
Immune Failure: This enzyme deficiency directly prevents the normal development of infection-fighting white blood cells, leaving the infant with a severely weakened immune system.
Infection Risk: Because the immune system is responsible for shielding the body from viruses, bacteria, and fungi, babies born with ADA-SCID are completely defenseless. For these infants, common, minor childhood infections can rapidly escalate and become life-threatening.
Prevalence and Genetics
Occurrence in Ireland: ADA-SCID is extremely rare, affecting approximately 1 in every 137,000 babies born in Ireland.
Inheritance Pattern: It is an autosomal recessive condition. This means an infant only develops ADA-SCID if they inherit two copies of the altered gene—one from each parent.
Role of the Heel Prick Screening
Because infants with ADA-SCID appear completely healthy at birth, early screening is vital to catch the condition before dangerous infections set in.
The Test: Screening for ADA-SCID is fully integrated into the standard newborn bloodspot (heel prick) screen, which is routinely administered when the infant is around 5 days old.
Collection: A qualified midwife or Public Health Nurse uses a specialized lancet device to collect a few drops of blood from the baby's heel onto a screening card.
Next Steps: If the laboratory analysis indicates that your baby is at risk or shows markers for ADA-SCID, you will be contacted immediately. The medical team will issue an urgent referral to a pediatric immunology specialistfor diagnostic testing and fast-tracked protective treatment.
2. Classical Galactosaemia (C Gal)
(C Gal) is a rare, inherited genetic condition that severely impairs a baby's ability to process galactose. Galactose is one of the two sugars that make up lactose, which is found naturally in human breast milk, cow's milk, and standard infant formulas.
C Gal is not a milk or lactose allergy. If a baby with C Gal consumes milk, toxic levels of galactose rapidly build up in their system, causing life-threatening complications.
Severe Risks of Delayed Diagnosis
If Classical Galactosaemia is not detected and managed immediately after birth, it can cause acute, catastrophic health issues, including:
Liver damage or acute liver failure
Sepsis (severe blood poisoning)
Brain hemorrhage (bleeding on the brain)
Cataracts (clouding of the eye lens, impairing vision)
Even with excellent lifelong management, some children may still face long-term health complications later in life, such as speech and developmental delays, dyspraxia (coordination issues), ataxia (balance and speech issues), brittle bones, delayed puberty, and female fertility challenges.
Targeted Screening Framework
Ireland utilizes a two-tier screening approach to catch C Gal as early as possible.
1. Universal Newborn Bloodspot (Heel Prick) Screening
All infants born in Ireland are universally screened for C Gal via the standard heel prick test between 3 and 5 days after birth.
2. The Beutler Test (Rapid Day-of-Birth Screening)
Because C Gal occurs with significantly higher frequency within the Irish Traveller community, infants born to Traveller parents are proactively offered the Beutler test. This test is also automatically fast-tracked for any newborn who has an older sibling diagnosed with C Gal.
Timing: Administered immediately on the day of birth.
Method: Performed as a rapid heel-prick sample at the hospital.
Turnaround: Results are processed with high urgency, typically returning within 2 to 3 days or sooner.
Critical Feeding Protocol During Screening
To guarantee infant safety while waiting for the Beutler test results, standard milk consumption must be completely paused.
Immediate Dietary Shift: Midwives will direct you to completely avoid breast milk and standard, lactose-based formulas. Your care team will provide specialized, galactose-free and lactose-free infant formulas (such as Nutramigen or Neocate) to use temporarily.
Preserving Breastfeeding: If you intend to breastfeed long-term, your midwife will provide practical guidance on hand-expressing and storing your breast milk safely while you await the test clearance.
Understanding the Results
If the Screen is Negative (C Gal is Absent)
You can immediately discontinue the specialized formula. If you wish to breastfeed, your midwife will assist you in transitioning your baby to the breast. If you prefer bottle-feeding, you can safely switch to your standard infant formula of choice.
If the Screen is Positive (C Gal is Diagnosed)
Your baby will be issued an immediate emergency referral to the National Centre for Inherited Metabolic Disorders (NCIMD).
Lifelong Management: The child must strictly maintain a 100% lactose-free and galactose-free diet for life.
Specialist Support: Clinical dietitians and metabolic specialists at the NCIMD will provide comprehensive, continuous education to help you manage your child's dietary and developmental needs.
3 Congenital Hypothyroidism (CHT)
CHT is a condition present from birth where a baby's body fails to produce sufficient amounts of a vital hormone called thyroxine. Thyroxine is a chemical manufactured by the thyroid gland, located in the neck, and is essential for a child's energy, brain development, and physical growth.
Causes and Strutural Deficiencies
Babies develop CHT due to one of three primary reasons:
The thyroid gland is underdeveloped or abnormally formed.
The thyroid gland is completely missing.
The thyroid gland is structurally present but fails to manufacture thyroxine.
In the vast majority of cases, CHT occurs spontaneously without a known cause. Only a very small percentage of cases are inherited from parents through genes.
Prevalence in Ireland
CHT is one of the more common conditions detected through newborn screening, affecting approximately 1 in every 1,000 babies born in Ireland.
Without early detection and intervention, the lack of thyroxine leads to severe growth failure, permanent intellectual disabilities, and developmental delays.
Diagnosis via the Heel Prick Test
Because infants with CHT rarely show any physical symptoms or obvious signs of hormone deficiency immediately after birth, early screening is crucial.
The Screening: Testing for CHT is a standard part of the universal newborn bloodspot (heel prick) screen, routinely performed when the baby is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet to collect a few drops of blood from the baby's heel onto a screening card.
Referral: If the laboratory analysis reveals low thyroxine levels or elevated thyroid-stimulating indicators, your baby will receive an immediate referral to a pediatric endocrinologist for diagnostic confirmation.
Treatment and Long-Term Outlook
If diagnostic testing confirms CHT, the treatment is straightforward, highly effective, and safe.
Hormone Replacement: Your baby will be prescribed a daily medication (levothyroxine) to replace the missing thyroxine hormone.
Normal Development: If this treatment is initiated promptly within the first few weeks of life, it completely prevents the risk of complications, allowing your baby to grow and develop perfectly normally.
Lifelong Care: Treatment for CHT is typically lifelong. Your medical team will schedule regular blood tests as your child grows to monitor their hormone levels and adjust the medication dosage appropriately.
4 Cystic Fibrosis (CF)
CF is an inherited genetic condition that causes certain organs, primarily the lungs and the digestive system, to produce thick, sticky mucus.
How CF Affects the Body
In a healthy body, mucus acts as a slippery lubricant. In individuals with CF, this secretion becomes abnormally dense and causes blockages:
Respiratory System: Thick mucus accumulates inside the lungs, trapping bacteria and leading to recurrent chest infections. Over time, these frequent infections cause progressive, irreversible lung damage.
Digestive System: The mucus plugs the narrow ducts of the pancreas, physically preventing essential digestive enzymes from reaching the small intestine. Consequently, infants with CF struggle to break down nutrients from food, often leading to poor weight gain and malnutrition despite a normal appetite.
Prevalence in Ireland
Ireland has one of the highest rates of Cystic Fibrosis in the world, with approximately 1 in every 2,100 babies born in the country diagnosed with the condition.
Universal Screening & The Two-Step Testing Process
Because early clinical intervention drastically improves nutritional status and preserves lung function, testing for CF is fully integrated into the standard newborn bloodspot screen.
Step 1: The Initial Heel Prick
When your baby is around 5 days old, a midwife or Public Health Nurse uses a specialized lancet to collect a few drops of blood from the infant's heel. The lab first screens this sample for elevated levels of a specific pancreatic protein (immunoreactive trypsinogen or IRT), which spills into the blood when the pancreatic ducts are blocked.
Step 2: Automatic Genetic Testing
If the initial protein screening indicates that your baby might be at risk for CF, the laboratory automatically initiates a follow-on screening test using the same blood sample. This second step is a targeted genetic test that looks for the most common gene mutations responsible for causing Cystic Fibrosis.
Clinical Limitations and Next Steps
If the Screen Suggests a High Risk
If the combined protein and genetic screening indicates a high probability of Cystic Fibrosis, your baby will be given an immediate referral to a pediatrician who specializes in Cystic Fibrosis. The specialist will perform definitive diagnostic testing—typically a painless sweat test that measures the amount of salt in the baby's perspiration—to confirm or rule out the diagnosis.
⚠️ Important Clinical Reminder: No screening system is flawless. The newborn bloodspot test cannot detect 100% of all Cystic Fibrosis cases. Even if your baby received a normal heel prick result, you should contact your GP immediately if your child exhibits any potential symptoms of CF, such as a persistent cough, recurrent chest infections, salty-tasting skin, or a consistent failure to gain weight.
5 Glutaric Aciduria Type 1 (GA1)
GA1 is an exceptionally rare, inherited genetic condition that impairs the body's ability to safely process proteins. It occurs when a vital metabolic enzyme called glutaryl-CoA dehydrogenase is either entirely missing or fails to function correctly.
Biological Impact and Health Risks
When you consume protein, your body breaks it down into smaller building blocks called amino acids. Because infants with GA1 lack the enzyme required to process certain amino acids (specifically lysine and tryptophan), these compounds and their toxic byproducts build up rapidly in the bloodstream and tissues.
Without early diagnosis and management, this toxic accumulation can cause catastrophic neurological complications, including:
Progressive, irreversible brain damage
Severe movement difficulties and loss of motor skills
Seizures or fits
Severe difficulty swallowing (dysphagia)
If left undetected, GA1 can cause sudden metabolic crises that are highly debilitating and life-threatening.
Prevalence and Genetics
Occurrence in Ireland: GA1 is extremely rare, affecting approximately 1 in every 85,000 babies born in Ireland.
Inheritance Pattern: It is an autosomal recessive condition. An infant only develops GA1 if they inherit two copies of the altered gene—one from each parent. The parents are typically unaffected carriers.
Diagnosis via Heel Prick Screening
Because newborns with GA1 appear completely healthy at birth, early universal screening is vital to protect the child before permanent brain damage occurs.
The Test: Screening for GA1 is fully integrated into the universal newborn bloodspot (heel prick) screen, routinely administered when the infant is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet to safely collect a few drops of blood from the baby's heel onto a screening card.
Urgent Referral: If laboratory analysis detects elevated levels of acylcarnitines or specific organic acids associated with GA1, your baby will receive an immediate, urgent referral to a pediatric metabolic specialist.
Lifelong Treatment and Outlook
If diagnostic testing confirms GA1, immediate and lifelong medical management is required to prevent metabolic crises.
Specialized Diet: Your baby will be placed on a strict, low-protein diet managed by clinical metabolic dietitians to limit the intake of harmful amino acids.
Medical Supplements: The child will be prescribed specialized amino acid formulas and protective medications (such as carnitine) to help clear toxic byproducts from the body.
Long-Term Outlook: If this comprehensive treatment protocol is initiated early—before any neurological damage occurs—your child can grow up to live a highly healthy, active, and fulfilling life.
6. Homocystinuria (HCU)
. Homocystinuria (HCU) is a rare, inherited genetic condition that causes a dangerous accumulation of specific amino acids in the blood. The disorder stems from an altered gene that prevents the body from correctly processing methionine, an amino acid found in protein-rich foods like meat and fish.
Health Risks and Complications
When the body cannot break down these protein building blocks, levels of homocystine and methionine spike throughout the system. Without early intervention, this toxic build-up can cause severe, long-term health complications, including:
Neurological Issues: Delays or impairments in normal brain development.
Cardiovascular Risks: An abnormally high risk of developing dangerous blood clots and experiencing early-onset strokes.
Skeletal Abnormalities: Bone disorders, structural weakness, or unusual lengthening of the bones.
Ocular Problems: Dislocation of the eye lenses and severe vision complications.
Prevalence and Genetics
Occurrence in Ireland: HCU affects approximately 1 in every 66,000 babies born in Ireland.
Inheritance Pattern: This is an autosomal recessive condition. An infant only develops HCU if they inherit two copies of the changed gene—one from each parent. The parents themselves are typically unaffected carriers.
Universal Heel Prick Screening
Newborns with HCU show no outward physical signs of the condition at birth. Universal screening is essential to identify the disorder before irreversible systemic damage occurs.
The Test: Screening for HCU is included in the newborn bloodspot (heel prick) screen, routinely performed when the infant is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet to collect a few drops of blood from the baby's heel onto a screening card.
Clinical Limitation: While the screen is highly effective at catching classic, severe HCU, milder variations of the condition may occasionally go undetected by standard bloodspot screening.
Specialist Referral: If the laboratory analysis identifies elevated methionine levels, your baby will be issued an immediate referral to a pediatric metabolic specialist for definitive diagnostic testing.
Lifelong Treatment and Management
If diagnostic tests confirm HCU, the child must immediately begin a strict, lifelong management plan to keep amino acid levels within a safe range.
Protein-Restricted Diet: A specialized, low-protein diet designed to severely limit the intake of natural methionine.
Nutritional Supplements: Because natural protein is restricted, the child will take specialized medical formulas containing essential vitamins, minerals, and alternative amino acids to ensure safe, healthy growth.
Medication: Targeted medications or high-dose vitamin therapies (such as Vitamin B6 or B12, depending on the specific type of HCU) may be prescribed to help the body process the amino acids safely.
Adhering strictly to this lifelong regimen drastically reduces the risk of your baby developing any of the skeletal, visual, or vascular complications associated with HCU.
7. Maple Syrup Urine Disease (MSUD)
MSUD is an exceptionally rare, inherited genetic condition that impairs the body's ability to process specific protein building blocks. The disorder gets its distinct name from a characteristic sweet, maple syrup-like odor that develops in an affected baby's urine.
Biological Impact and Severe Risks
When we consume protein-rich foods like meat, fish, and dairy, the body breaks them down into smaller compounds called amino acids.
The Defect: Infants born with MSUD lack the essential enzyme complex required to process three specific amino acids: leucine, isoleucine, and valine.
Toxic Build-up: Consequently, these amino acids and their dangerous byproducts accumulate rapidly in the blood, tissues, and urine.
Acute Complications: Without immediate intervention, this toxic buildup triggers a severe metabolic crisis within just a few days of birth, leading to seizures (fits), comas, irreversible brain damage, and severe developmental delays. Left untreated, the condition is rapidly life-threatening.
Prevalence and Genetics
Occurrence in Ireland: MSUD is extraordinarily rare, affecting approximately 1 in every 460,000 babies born in Ireland.
Inheritance Pattern: It is an autosomal recessive condition. A newborn only develops MSUD if they inherit two copies of the altered gene—one from each parent. The parents are typically unaffected carriers.
Universal Screening via the Heel Prick Test
Because MSUD can cause catastrophic damage within the first week of life, rapid universal screening is essential to catch the condition before a metabolic crisis occurs.
The Procedure: Testing for MSUD is fully integrated into the standard newborn bloodspot (heel prick) screen, routinely administered when the infant is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet device to safely collect a few drops of blood from the baby's heel onto a screening card.
Urgent Referral: If the laboratory analysis identifies elevated levels of the branched-chain amino acids associated with MSUD, your baby will receive an immediate, high-priority referral to a pediatric metabolic specialist.
Clinical Limitation: Standard bloodspot screening is highly effective at catching classic, severe neonatal MSUD. However, milder or intermittent variations of the condition may not be detected by newborn screening because their symptoms can develop later in childhood or adulthood.
Lifelong Treatment and Medical Outlook
If diagnostic testing confirms MSUD, immediate and lifelong medical management must be sustained to prevent neurological complications and keep amino acid levels within a safe range.
Protein-Restricted Diet: Your child must adhere strictly to a specialized, low-protein diet managed by clinical metabolic dietitians to limit the intake of leucine, isoleucine, and valine.
Nutritional Supplements: Because natural protein intake is strictly restricted, the child will consume a specialized amino acid medical formula fortified with essential vitamins, minerals, and alternative amino acids to support safe, healthy growth.
Medical Outlook: If this precise dietary protocol is initiated early—before any neurological damage occurs—your child will typically experience normal brain development and enjoy excellent long-term health.
8. Medium-Chain Acyl-CoA Dehydrogenase Deficiency (MCADD)
(MCADD) is a rare, inherited genetic condition that affects how a baby's body breaks down fats to use as energy.
Prevalence and Genetics
Occurrence in Ireland: MCADD affects approximately 1 in every 17,000 babies born in Ireland.
Inheritance Pattern: This is an autosomal recessive disorder. An infant only develops MCADD if they inherit two copies of the altered gene—one from each parent. The parents themselves are typically unaffected carriers.
How the Body is Affected
Normally, when the body runs out of energy from sugars (such as during long periods without food), it breaks down fat stores for fuel.
The Defect: Babies with MCADD lack an essential enzyme needed to convert medium-chain fatty acids into energy.
The Risk: Without this enzyme, fasting or illness can cause their blood sugar levels to drop dangerously low (hypoglycemia), and toxic byproducts can accumulate in the body. If left untreated, this can lead to severe metabolic crises, seizures, comas, or sudden death.
Universal Screening via the Heel Prick Test
Because infants with MCADD look completely healthy at birth, early universal screening is vital to identify the condition before a metabolic crisis occurs.
The Procedure: Testing for MCADD is fully integrated into the standard newborn bloodspot (heel prick) screen, routinely performed when the infant is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet device to safely collect a few drops of blood from the baby's heel onto a screening card.
Specialist Referral: If the laboratory analysis identifies markers indicating a high risk of MCADD, your baby will receive an immediate referral to a pediatric metabolic specialist for definitive diagnostic testing.
Medical Outlook: If the condition is detected early and properly managed, your child can lead a perfectly healthy, active, and normal life.
Red Flag Symptoms: When to Seek Urgent Care
This information is for general knowledge and should not be taken as medical advice. Consult with a healthcare provider before starting any new treatment or managing medical conditions.
In exceptionally rare instances, a newborn may become unwell and show symptoms of MCADD before the heel prick test is administered or before the results are returned.
Contact your GP or seek immediate emergency medical care if your newborn exhibits any of the following warning signs:
Extreme drowsiness or difficulty waking up
Poor feeding or refusing to feed
Frequent vomiting
Unusually low energy or lethargy
Seizures or fits
9. Phenylketonuria (PKU)
(PKU) is a rare, inherited genetic condition that affects the body's ability to break down a specific amino acid called phenylalanine, which is found in protein-rich foods and some artificial sweeteners. The disorder occurs because a vital liver enzyme—phenylalanine hydroxylase—is either completely missing or not functioning correctly.
Biological Impact and Health Risks
When a baby with PKU consumes protein, phenylalanine cannot be processed normally and builds up to dangerous levels in the blood and brain tissue. Without early diagnosis and treatment, this toxic accumulation causes severe, irreversible complications, including:
Severe intellectual disabilities
Permanent brain damage
Behavioral problems and developmental delays
Neurological issues, including seizures
Prevalence in Ireland
PKU has a relatively high prevalence in Ireland compared to many other countries, affecting approximately 1 in every 4,000 babies born in the country.
Diagnosis via Heel Prick Screening
Because infants with PKU show no physical symptoms or outward signs of the condition at birth, universal screening is crucial to intervene before brain damage begins.
The Test: Screening for PKU is a standard component of the newborn bloodspot (heel prick) screen, routinely performed when the baby is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet to collect a few drops of blood from the baby's heel onto a screening card.
Immediate Referral: If the laboratory analysis identifies elevated phenylalanine levels, your baby will be issued an immediate referral to a pediatric metabolic specialist for diagnostic confirmation.
Lifelong Treatment and Management
If diagnostic testing confirms PKU, treatment begins immediately to keep phenylalanine levels within a safe target range.
Specialised Diet: Your child must follow a strict, low-protein diet managed by clinical metabolic dietitians. This requires avoiding high-protein foods like meat, fish, dairy, eggs, nuts, and seeds.
Nutritional Supplements: Because natural protein is restricted, your baby will take a special phenylalanine-free amino acid formula fortified with essential vitamins, minerals, and other nutrients required for healthy growth.
Regular Monitoring: The child will need regular, ongoing blood tests—often weekly during infancy—to track phenylalanine levels and allow doctors to adjust the diet as they grow.
Long-Term Outlook: If this dietary management is started early and maintained strictly throughout life, the toxic buildup is prevented, allowing most children to develop normally and live healthy, active lives.
10. Severe Combined Immunodeficiency (SCID)
(SCID) is a rare, inherited genetic condition passed from parents to their children. It is a highly serious disorder that causes a profound failure of the child's immune system, leaving them extremely vulnerable to illness.
Biological Impact and Health Risks
The condition occurs because a genetic mutation prevents the body from developing functioning T-cells, which are vital white blood cells responsible for identifying and destroying pathogens.
Immune Failure: Without adequate T-cells, infants born with SCID possess a severely compromised immune system and are completely defenseless against viruses, bacteria, and fungi.
Infection Risk: Because their bodies cannot mount an immune response, common, minor childhood infections can rapidly escalate and become life-threatening if left untreated.
Prevalence in Ireland
Occurrence: SCID is rare, affecting approximately 1 in every 40,000 babies born in Ireland.
Genetic Variance: The general term SCID encompasses several distinct genetic mutations. This includes ADA-SCID (Adenosine Deaminase Deficiency SCID), which is a specific, separate type of SCID also included in the Irish screening programme.
Diagnosis via Heel Prick Screening
Because infants with SCID appear completely healthy at birth, early universal screening is vital to catch the condition before dangerous environmental infections set in.
The Test: Screening for SCID is fully integrated into the standard newborn bloodspot (heel prick) screen, routinely administered when the infant is around 5 days old.
Collection: A midwife or Public Health Nurse uses a specialized lancet device to safely collect a few drops of blood from the baby's heel onto a screening card.
Next Steps: If the laboratory analysis identifies low immune markers or a lack of T-cell development, you will be contacted immediately. The medical team will fast-track your baby for diagnostic testing to confirm or rule out the condition.
Urgent Treatment and Medical Outlook
If diagnostic testing confirms SCID, the infant will receive an immediate hospital admission for urgent, life-saving corrective treatment. Starting treatment as early as possible dramatically increases the baby's chances of a full recovery.
Bone Marrow Transplant: A procedure to transplant healthy stem cells from a donor to rebuild the infant's missing immune system.
Gene Therapy: An advanced medical treatment that corrects the faulty gene inside the child's own cells (available for specific types of SCID).
Clinical Support: A dedicated specialist team of pediatric immunologists will support your family, manage protective isolation measures to keep your baby safe from germs, and explain all available treatment options.
11. Spinal Muscular Atrophy (SMA)
SMA is a rare, inherited genetic condition passed from parents to their children. It impairs the nervous system, leading to progressive muscle weakness, motor challenges, and in severe forms, life-threatening complications.
Biological Impact and Health Risks
The disorder is caused by a genetic mutation that prevents the body from producing sufficient amounts of a vital protein called Survival Motor Neuron (SMN) protein.
Cell Degeneration: SMN protein is indispensable for the health and survival of motor neurons—the specialized nerve cells in the spinal cord that connect to and control muscles.
Muscle Wasting: Without adequate levels of this protein, these nerve cells wither and die. This disrupts the signals traveling from the brain to the muscles, causing progressive muscle wasting (atrophy), weakness, and difficulties with breathing, swallowing, and movement.
Prevalence in Ireland
SMA affects approximately 1 in every 9,000 babies born in Ireland. While there is currently no definitive cure for the condition, early clinical intervention can fundamentally alter the trajectory of the disease, drastically improving a child's health, milestones, and overall quality of life.
Diagnosis via Heel Prick Screening
Because infants with SMA often appear entirely healthy at birth, universal screening is critical to identify the condition and initiate treatment before irreversible motor neuron damage occurs.
The Test: Screening for SMA is fully integrated into the standard newborn bloodspot (heel prick) screen, routinely performed when the baby is around 5 days old.
Genetic Analysis: Unlike some other components of the bloodspot panel that look for metabolic proteins, the screening test for SMA is a targeted genetic test that directly analyzes the infant's DNA for the missing or altered SMN gene.
Collection: A midwife or Public Health Nurse uses a specialized lancet device to safely collect a few drops of blood from the infant's heel onto a screening card.
Next Steps and Treatment Options
If the laboratory analysis identifies markers indicating that your baby is at risk for SMA, a specialist team will contact you immediately to arrange diagnostic confirmation tests.
Urgent Hospital Care: If the diagnosis is confirmed, your baby will be fast-tracked for urgent hospital treatment. The earlier treatment is initiated—ideally before any physical symptoms emerge—the better the long-term developmental outcomes for the child.
Advanced Therapies: While there is no cure, highly effective, advanced therapies (such as disease-modifying gene therapies or targeted medications that boost SMN protein production) are available to protect motor neurons.
Comprehensive Support: A multidisciplinary specialist team will support your family, coordinate therapies, and detail the best treatment options available to maximize your baby's physical development and quality of life.
The newborn bloodspot screening, or heel prick screen, is a routine health check performed shortly after birth. It collects a small blood sample to screen your infant for 11 rare but serious conditions, enabling early intervention if an increased risk is detected.
Test Logistics and Comfort Tips
The screening is performed by a midwife or Public Health Nurse (PHN) either in the hospital or at your home, typically 3 to 5 days after birth. The practitioner uses a specialized lancet to collect a few drops of blood from the infant's heel onto a newborn bloodspot screening card.
To help the procedure go smoothly and maximize your baby's comfort:
Ensure the infant is warm and physically comfortable before the test.
Warm their feet: Dress the baby in two pairs of socks during the hour leading up to the appointment to increase peripheral circulation.
Be ready to immediately feed, hold, or soothe your baby once the sample collection is complete.
Informed Consent Requirements
Who Can Authorise the Test
Only a child's legal guardian can provide consent for the screening.
The birth mother is automatically a legal guardian.
A married father is also a legal guardian.
For same-sex female couples, the female partner may give consent if they have established legal guardianship under specific circumstances.
In most other situations, unmarried partners or relatives do not hold legal guardianship at the time of screening and cannot authorize the test. If you are uncertain of your legal status, clarify it with your healthcare provider before the appointment.
Giving Consent
You grant authorization by signing the physical newborn screening card. If you are physically unable to sign, you can provide verbal consent or make a mark on the card in the presence of the midwife or PHN. By signing, you confirm that:
You are the baby's legal guardian.
You have read, understood, and accepted the screening educational materials.
All handwritten baby and parental information on the card is correct.
You consent to the laboratory tests, which automatically include genetic testing for Spinal Muscular Atrophy (SMA) and may include a secondary genetic test for Cystic Fibrosis (CF) if early protein markers are elevated.
You agree to the safe storage of the card and associated data for a standard duration of 10 years.
Structure and Journey of the Screening Card
The specialized card consists of three distinct parts: a blood spot sample collection grid, an information and consent logging sheet, and a carbon copy duplicate of the information sheet for the parents' personal records.
Once the sample is collected, it follows a strict processing pathway:
Secure Data and Sample Management
Storage Limit: The National Newborn Bloodspot Screening Laboratory secures the card in a restricted facility for 10 years, after which it is destroyed.
System Program Growth: If new conditions are added to the national panel in the future, older stored samples may be run to validate the efficacy of the new tests. In these instances, all samples are completely anonymized—names are stripped, and the material can never be linked back to your child.
Commercial Protection: Samples are strictly prohibited from being sold or used for commercial purposes.
Clinical Health Records: Health services securely store the screening card information and numerical results to maintain clinical continuity. This data is only used to contact you if a repeat sample is needed due to an insufficient initial blood volume or an unclear laboratory result. Anonymized data is also shared for international healthcare quality assurance.
Audit and Review: If a child is later diagnosed with a condition that slipped through the screen, their physician will contact the lab to audit the original card. If an error is identified, you will be notified immediately.
Opting Out and Changing Your Mind
While health authorities strongly recommend this screen to prevent severe childhood disability or death, participation is entirely voluntary.
To Opt Out: Inform your midwife or PHN during the screening offer. You will be required to sign an official opt-out form confirming that you fully understand the medical risks of leaving these 11 conditions unscreened.
Reversing Your Decision: If you initially decline the test but change your mind later, you can contact your GP or local PHN to arrange a catch-up screen. The test can be safely administered at any point up until the child reaches 12 months of age.
The results of the newborn bloodspot (heel prick) screen fall into two main categories: normal ("not suspected") or positive ("suspected"). Because screening tests act as a preliminary filter rather than a definitive diagnosis, a small percentage of results may be classified as false positives or false negatives upon further clinical testing.
Normal ("Not Suspected") Screening Results
The vast majority of infants screened will receive a normal or negative screening result.
What It Means: A normal result indicates that your baby is at low risk and is not suspected of having any of the 11 screened conditions.
Communication Protocol: Health services will not contact you if your baby's results are normal. If you wish to view the documentation for your records, you can request the results directly from your Public Health Nurse (PHN).
Clinical Disclaimer: A normal screening result is not a absolute guarantee of health. If your child later develops symptoms or you have any concerns regarding their physical development, contact your GP or PHN immediately.
Positive ("Suspected") Screening Results
If laboratory analysis detects biochemical or genetic markers for any of the 11 conditions, the result is flagged as positive.
Communication Protocol: A doctor or nurse will contact you directly, typically within a few days of the sample being sent to the laboratory.
Not a Final Diagnosis: A positive screening result is not a diagnosis. It simply means your baby shows an increased risk for a condition and requires immediate, definitive diagnostic tests.
Next Steps: Your baby will be fast-tracked for diagnostic testing to confirm or rule out the disorder. Depending on the condition suspected, your baby may be admitted to the hospital during this brief testing period.
If the Condition is Confirmed: Your baby will receive an immediate referral to a dedicated specialist centre. A multidisciplinary medical team will work closely with your family to implement early treatments and long-term health support.
Understanding Screening Limitations
No screening test is flawless. False positives and false negatives are unavoidable limitations inherent to all mass screening programmes. The National Healthy Childhood Programme monitors these occurrences closely and publishes the exact figures annually in its Screening Programme's Annual Report.
1. False Positive Results
Definition: The initial heel prick test indicates the baby is at risk (positive result), but subsequent, high-precision diagnostic tests confirm the baby is entirely healthy and does not have the condition.
Impact: While receiving a positive notification is highly stressful for parents, the follow-up diagnostic testing is the only way to rule out the condition and ensure the baby's safety.
2. False Negative Results
Definition: The initial heel prick screen indicates the baby is healthy (normal result), but the baby does, in fact, have the condition.
Impact: False negatives are exceptionally rare. If a child is later diagnosed with a panel condition that the screen missed, the managing physician will notify the national laboratory. The lab will audit the original screening card to determine if a procedural issue occurred, and the findings will be shared with the family.
Disclaimer
The information provided here is for educational and informational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional or your GP for specific medical concerns, diagnoses, or health advice. Never disregard professional medical advice or delay seeking it because of information you have read here.